Topical Oxygen Therapy for Wound Bed Optimization Prior to Planned Skin Substitute Application: A Four-Patient Case Series
Last updated:
Poster Authors: Edward C. Kormylo, DPM, FACFAS; Momina Tariq, DPM; Syed Zain Huda, DPM; Deep Kumar, DPM
100% of patients showed improved
wound bed characteristics
50% achieved full wound closure —
skin substitutes/grafts not needed
SUMMARY
This four-patient case series, conducted at NYU Grossman Long Island School of Medicine, evaluated NATROX® O₂ Continuous Topical Oxygen Therapy (cTOT) as an adjunct therapy for complex lower-extremity wounds that had stalled despite standard care and were being prepared for skin grafts or skin substitutes. All four patients showed measurable improvement in wound bed quality. Two patients healed to full closure during wound bed preparation — eliminating the need for the planned skin substitute/graft entirely.
Four Patient Case Series

Case 1: Chronic diabetic/Charcot foot wound
Case 2: Full-thickness plantar ulcer with PAD
Case 3: Chronic rearfoot ulcer with osteomyelitis history
Case 4: High-risk surgical candidate with bilateral wounds
Active healing — ongoing improvement
Results
All four patients demonstrated favorable clinical progression following incorporation of Continuous Topical Oxygen Therapy (cTOT). Across the series, wounds showed increased healthy granulation tissue, reduced devitalized tissue, improved wound edge stability, and overall wound bed optimization despite varied etiologies and comorbidities.
Two of four patients (50%) achieved complete wound closure during continued wound bed preparation, eliminating the need for their originally planned graft or skin substitute.
The remaining two patients demonstrated ongoing improvement in granulation tissue and wound bed quality and remain actively healing. Individual wound responses included progressive granulation and coverage in a postoperative wound dehiscence; improved depth, granulation, and stability in diabetic and venous ulcers; rapid granulation and wound contraction in a full-thickness ulcer following bone excision; and stable granulation with progressive coverage of exposed muscle and bone in complex bilateral wounds.
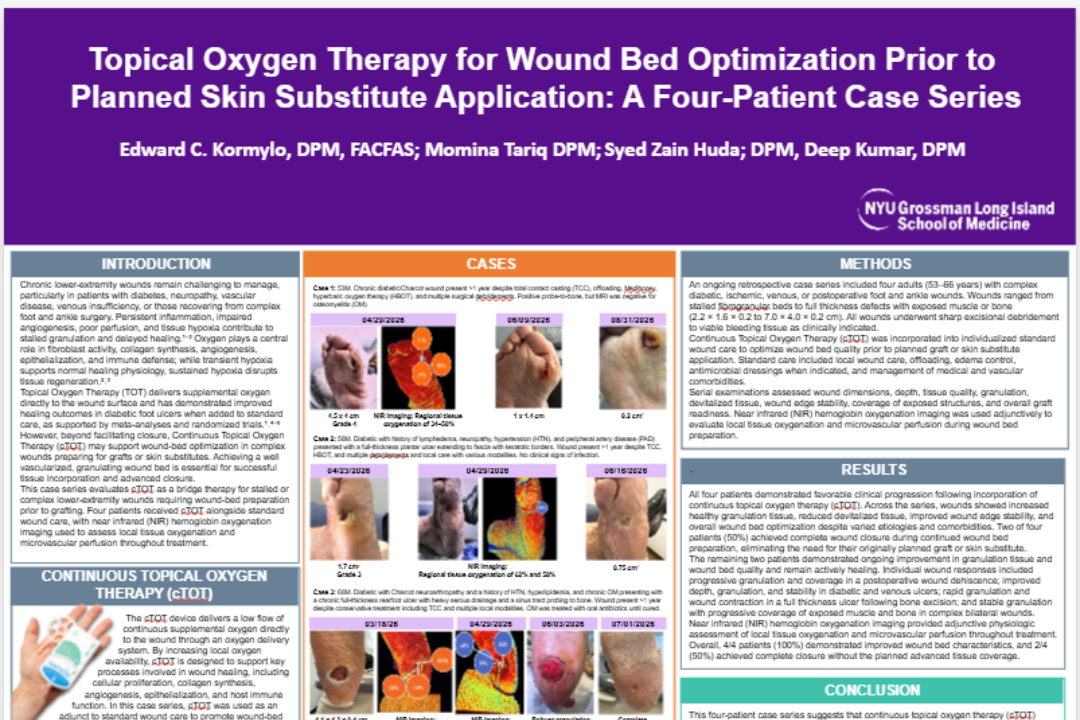
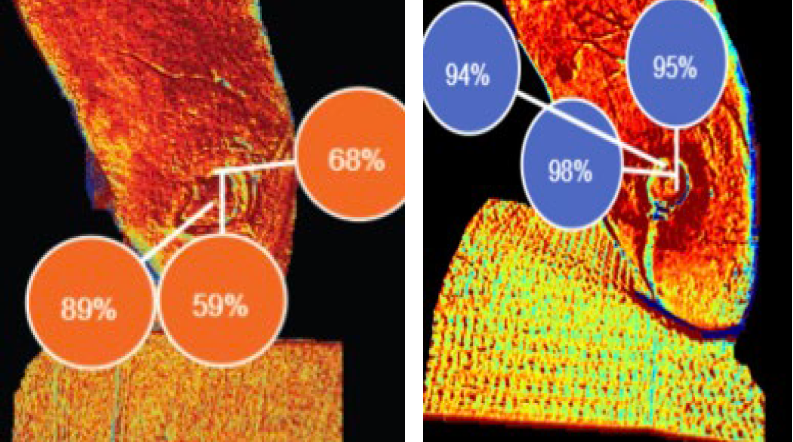
Near infrared (NIR) hemoglobin oxygenation imaging provided adjunctive physiologic assessment of local tissue oxygenation and microvascular perfusion throughout treatment. Overall, 4/4 patients (100%) demonstrated improved wound bed characteristics, and 2/4 (50%) achieved complete closure without the planned advanced tissue coverage.
How NATROX® O₂ supports wound bed preparation
Beyond facilitating closure, Continuous Topical Oxygen Therapy (cTOT) may support wound bed optimization in complex wounds preparing for grafts or skin substitutes. Achieving a well-vascularized, granulating wound bed is essential for successful tissue incorporation and advanced closure.
(See baseline image and 6 weeks progress from Case 3)
What does this mean for your clinical practice?
This four-patient case series suggests that Continuous Topical Oxygen Therapy (cTOT) may support wound bed optimization in complex lower extremity wounds preparing for graft or skin substitute application. Despite substantial healing barriers—including diabetes, vascular disease, postoperative dehiscence, complex foot deformities (Charcot arthropathy) and exposed deep structures—all patients demonstrated progressive improvement in granulation tissue, wound edge stability, and overall wound bed viability following incorporation of cTOT into a comprehensive wound care management plan. By addressing local hypoxia, cTOT functioned as a bridge therapy to establish receptive wound beds for advanced closure procedures.
Two patients progressed to full closure during adjunctive treatment with cTOT, eliminating the need for further intervention with grafting or skin substitutes. The remaining patients continued to show clinical improvement to granulation tissue and coverage of exposed structures. Near-infrared spectroscopy (NIRS) hemoglobin oxygenation imaging provided complementary physiologic insight into local tissue oxygenation and microvascular perfusion, aligning with observed clinical improvements in wound bed quality. These findings support further investigation of cTOT as a tool for targeted wound bed optimization in preparation for successful advanced wound closure.
This poster was presented at SAWC Fall 2026 in Las Vegas, Nevada.